
The Comprehensive Guide to Modern Diets: What Actually Works in 2026

- What Do the New 2025–2030 Dietary Guidelines Actually Say?
- What Is a “Modern Diet” and Why Does It Matter?
- How Do the Major Diet Frameworks Differ?
- When Is a Diet a Clinical Decision Rather Than a Lifestyle Choice?
- What Are the Major 2025–2026 Diet Trends Worth Paying Attention To?
- How Do You Actually Build a Diet That Works for You?
- What Are the Most Common Diet Mistakes Adults Make?
- How Does Inflammation Fit Into Modern Diet Thinking?
- Diet Finder: A Practical Starting Checklist
- Conclusion: What to Actually Do Next
Last updated: October 26, 2026
Quick Answer: There is no single best diet for everyone. A practical starting point is a varied pattern built around foods you can afford, prepare, and enjoy, while respecting any medical context. Current U.S. dietary guidance is a broad food-pattern framework—not a one-size-fits-all prescription.[1]
Key Takeaways
- The 2025–2030 Dietary Guidelines for Americans, released in January 2026, use “eat real food” as a central framing for a whole-food dietary pattern.[1]
- No single named diet is the right fit for everyone. A useful choice has to work with a person’s preferences, budget, culture, cooking skills, and health context.
- The Guidelines include a protein-food serving goal, whole grains, fruit and vegetables, dairy or fortified alternatives, and plant proteins such as beans, lentils, nuts, seeds, and soy.[1]
- DASH has a specific blood-pressure focus; people with chronic kidney disease or on dialysis need individual advice rather than a generic plan.[3][4]
- GLP-1 nutrition, time-restricted eating, consumer CGMs, and longevity claims need more caution than social-media summaries usually provide.[5][6]
What Do the New 2025–2030 Dietary Guidelines Actually Say?
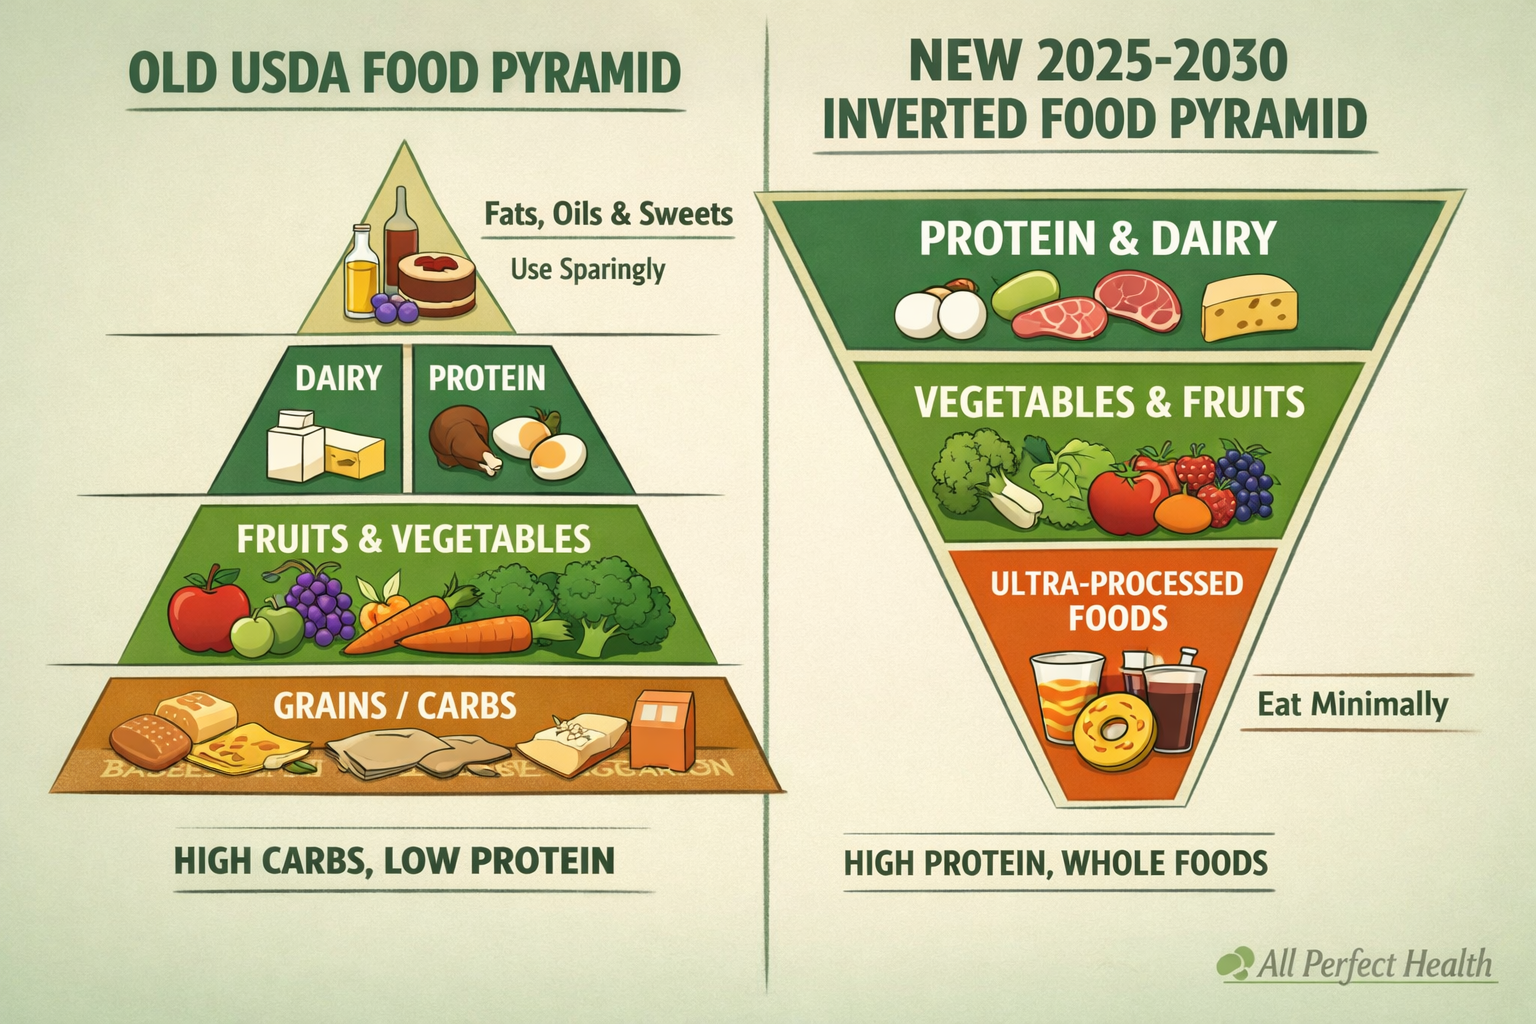
The 2025–2030 Dietary Guidelines for Americans were released in January 2026. Their broad message is to build meals around nutrient-dense foods and limit added sugars, refined carbohydrates, and chemical additives.[1]
Protein is one part of the food pattern, not a universal prescription. The Guidelines describe a protein-food serving goal of 1.2–1.6 grams per kilogram of body weight per day. That food-pattern goal does not replace the separate Dietary Reference Intake system or individual clinical advice.
Whole grains and plant foods remain in the pattern. The Guidelines include whole grains, fruit, vegetables, dairy or fortified alternatives, and protein foods from both animal and plant sources, including beans, peas, lentils, legumes, nuts, seeds, and soy. Fresh, frozen, and canned vegetables can all fit when their ingredients suit the overall pattern.[1]
Fat quality still matters. The Guidelines include unsweetened full-fat dairy and cooking fats while prioritising oils with essential fatty acids. They also retain the general advice that saturated fat should not exceed 10% of total daily calories.[1] The 2020–2025 Guidelines were not a blanket low-total-fat plan; they focused on dietary patterns and limiting saturated fat.[2]
These Guidelines are a population-level framework, not a diagnosis or a personalised eating plan. Medical diets, medication use, kidney disease, pregnancy, eating-disorder history, and other clinical contexts need individual guidance.
What Is a “Modern Diet” and Why Does It Matter?
In plain English, a modern diet is a current way of organising food choices. It may be a broad eating pattern, a change to carbohydrate or protein intake, a timing practice, or a clinical restriction. The useful question is not which label is “best”; it is what changes, what trade-offs follow, and whether the approach fits a person’s life.
Perspective: This video is commentary, not a replacement for the sources and clinical boundaries in this guide.
The basics still do the heavy lifting. A practical pattern generally includes foods a person can afford and prepare, adequate nourishment, and room for their preferences. A named diet should make those basics easier, not turn food into a constant test.
How Do the Major Diet Frameworks Differ?
These labels describe different ways of organising food. They are not rankings or treatment plans. The table is a starting comparison; it cannot decide what is appropriate for an individual.
| Diet pattern | What it mainly changes | Useful decision question | Practical watch-out |
|---|---|---|---|
| Mediterranean-style | Emphasises vegetables, fruit, legumes, whole grains, fish, olive oil, and other minimally processed foods. | Do you want a flexible food-pattern approach rather than a strict rule set? | It still needs to fit budget, culture, cooking skills, and personal preferences. |
| DASH | Builds meals around fruit, vegetables, grains, low-fat dairy, and lower sodium. | Is blood-pressure management part of the conversation with your clinician? | People with CKD or on dialysis should not start standard DASH without individual medical or renal-dietitian guidance.[3][4] |
| Plant-forward or plant-based | Puts plant foods at the centre; strict versions exclude some or all animal foods. | Does the pattern fit your values and everyday food access? | More restrictive versions need deliberate attention to nutrients such as vitamin B12. |
| Lower-carbohydrate or ketogenic | Reduces carbohydrate foods to different degrees; ketogenic approaches are more restrictive. | Can you sustain the food rules without making eating socially or nutritionally harder? | Medication use and diagnosed conditions need clinician input; this page does not prescribe a carbohydrate target. |
| Higher-protein | Puts more emphasis on protein foods within an overall diet. | Is protein adequacy a practical concern for your appetite, activity, or food pattern? | A grams-per-kilogram target is not a universal recommendation, particularly with kidney disease. |
If weight loss is your primary goal, use the separate Best Weight Loss Diet guide for that decision. It has a different job from this broad comparison page.
Readers exploring a lower-carbohydrate route can also review APH’s Low Carb Diet for Weight Loss guide; use it as background information, not a substitute for care when medication or a diagnosed condition is involved.
1. Mediterranean-style eating: a flexible pattern, not a fixed menu
What changes: the pattern places vegetables, fruit, legumes, whole grains, olive oil, nuts, and seafood at the centre, with room for individual culture and preferences.
What day-to-day life can look like: meals are built from ordinary whole foods rather than a strict exclusion list. The practical question is whether those foods are accessible and enjoyable enough to repeat.
What the evidence can—and cannot—say: in a reanalysed PREDIMED trial of Spanish adults at high cardiovascular risk, participants assigned to a Mediterranean pattern supplemented with extra-virgin olive oil or nuts had fewer major cardiovascular events than those given reduced-fat-diet advice.[7] That is meaningful evidence for that population and comparison; it does not make Mediterranean eating the only reasonable pattern or a personal treatment plan.
Useful next step: APH’s Mediterranean Food guide can help readers picture the foods without treating the label as a rulebook.
2. DASH: a structured food pattern with a blood-pressure context
What changes: DASH emphasises fruit, vegetables, grains, dairy, protein foods, and lower sodium.[3] It is more structured than “eat healthier,” but it is still a food pattern rather than a one-size-fits-all renal diet.
What day-to-day life can look like: regular meals use a range of produce, grains, protein foods, and dairy or alternatives while attention is paid to sodium. This can be practical for some households and more demanding for people who rely heavily on restaurant or packaged foods.
Boundary: people with chronic kidney disease or on dialysis should not treat standard DASH as automatic advice; kidney-related nutrition can require individual modification.[4]
3. Plant-forward, vegetarian, and vegan patterns: restriction changes the planning job
What changes: plant-forward eating can simply mean more plant foods, while vegetarian and vegan patterns progressively limit or remove animal foods. Those are different levels of restriction and should not be treated as interchangeable.
What day-to-day life can look like: legumes, grains, vegetables, fruit, nuts, seeds, and soy foods may carry more of the meal structure. The more foods a pattern excludes, the more intentional the nutrient planning needs to become.
Evidence and trade-off: a well-designed vegetarian pattern can meet nutritional needs, but vitamin B12 needs specific attention—particularly with vegan eating.[8] “Plant-based” is not automatically nutritious, and it is not automatically inadequate either; the details matter.
4. Lower-carbohydrate and ketogenic patterns: the degree of restriction matters
What changes: lower-carbohydrate patterns reduce carbohydrate foods to different degrees. A ketogenic pattern is more restrictive than a general lower-carbohydrate approach, so the food choices, social friction, and medical implications are different.
What day-to-day life can look like: these patterns tend to shift meals toward protein foods, fats, and lower-carbohydrate vegetables while limiting some grains, fruit, legumes, or starchy foods depending on the version.
Evidence and trade-off: a 2025 meta-analysis in adults with type 2 diabetes found modest short-term glycaemic benefits from low-carbohydrate diets, with benefits diminishing over time and definitions varying across studies.[9] That is not a reason to change diabetes medication or self-prescribe ketosis; medication use and diagnosed conditions need clinician input.
5. Higher-protein patterns: a lever, not a universal number
What changes: the focus is on making protein foods a more deliberate part of meals within an otherwise varied diet.
What day-to-day life can look like: rather than chasing a single number, readers can consider whether meals regularly include protein foods they tolerate, enjoy, and can afford. The 2025–2030 Guidelines include a protein-food serving goal, but an article cannot set a personal target for every reader.[1]
Boundary: higher-protein is not automatically better, especially where kidney disease or another medical condition changes the nutrition conversation.
6. Time-restricted eating: a schedule tool, not a food-quality shortcut
What changes: time-restricted eating limits the eating window rather than assigning foods as good or bad.
What day-to-day life can look like: it may simplify some people’s routine, but it can make shared meals, training, medication schedules, or adequate food intake harder for others.
Evidence and trade-off: a recent systematic review compared time-restricted eating with both isocaloric and non-isocaloric controls, underscoring why it is too simple to credit any result solely to the clock rather than total intake, adherence, or study design.[10] Fasting is not appropriate for everyone.
7. Carnivore and elimination approaches: distinguish experience reports from outcome evidence
What changes: carnivore patterns eliminate most or all plant foods; elimination diets remove selected foods for a defined reason. Both are far more restrictive than a general whole-food pattern.
What day-to-day life can look like: the narrow food list can feel simple initially, but it also reduces flexibility, changes nutrient planning, and makes a broad promise from a very limited experiment tempting.
Evidence and trade-off: the often-cited 2021 carnivore paper was an online survey of self-selected adults; it reported participants’ experiences but also states important risks of recall, reporting, and selection bias, and cannot establish long-term safety or disease treatment.[11] Readers considering a restrictive experiment can review APH’s Carnivore Diet guide and Elimination Diet guide before making a major change.
Seven questions that make the comparison useful
- What does this pattern actually ask me to eat more of, less of, or exclude?
- What evidence exists for the outcome I care about—and in what population?
- What practical friction will it create for budget, cooking, travel, family meals, and social life?
- What nutrients or food groups need extra planning because of the restriction?
- Can I describe the pattern without using a claim that it cures, reverses, or guarantees anything?
- Does this overlap with a medical or medication decision that requires individual advice?
- Could I still follow the useful part of the pattern in six months?
When Is a Diet a Clinical Decision Rather Than a Lifestyle Choice?
General diet comparisons are not the same as medical nutrition therapy. A pattern may be reasonable as general education while still being the wrong place to make an individual decision.
- Kidney disease or dialysis: standard DASH and higher-protein approaches may need individual modification.[4]
- Diabetes medication or other prescription medicines: a major shift in carbohydrate intake, fasting, appetite, or weight can change the clinical context. Do not use this guide to adjust medicines.
- Pregnancy, breastfeeding, eating-disorder history, unexplained weight change, or persistent symptoms: restrictive plans deserve professional guidance rather than a generic checklist.
- Therapeutic ketogenic or elimination diets: these are different from casual online challenges and should not be copied as treatment protocols.
This is not a warning against curiosity. It is a reminder to match the decision to the level of risk.
What Are the Major 2025–2026 Diet Trends Worth Paying Attention To?

This is where hype can get in the way. A trend can be interesting without being a proven answer for everyone.
1. Nutrition alongside GLP-1 therapy
There is no single standard “GLP-1 diet.” A 2025 joint advisory highlights the importance of assessing usual food intake, preventing nutritional deficiencies, preserving muscle and bone, and using resistance training and appropriate diet alongside medical care.[5] Medication choices and dose changes belong with the prescribing clinician; a registered dietitian can help make food changes fit the individual.
2. Time-restricted eating
Time-restricted eating changes when someone eats, not necessarily what they eat. It may suit some schedules, but it is not a treatment and no one eating window is right for everyone. Anyone who is pregnant or breastfeeding, has an eating-disorder history, uses glucose-lowering medication, or has another relevant medical concern should seek individual advice before fasting.
For a fuller introduction to the practice, see APH’s Intermittent Fasting for Weight Loss guide.
3. CGM-guided eating
In people without diabetes, a 2026 systematic review found that CGM can help with short-term dietary behaviour and adherence, but is unlikely to achieve weight-management goals on its own without behavioural support.[6] Normal after-meal changes are not, by themselves, a diagnosis. A CGM is information, not a verdict on a food or a person.
4. “Longevity” eating
Diet patterns can be studied alongside cardiometabolic markers and long-term health outcomes, but no named “longevity diet” has proved that it extends human lifespan. The sensible focus is an overall food pattern a person can sustain, not a single food, supplement, or fasting protocol.
How Do You Actually Build a Diet That Works for You?

This is the practical core of a modern diet comparison. The aim is to find a pattern that is nourishing, realistic, and safe in your circumstances—not to follow the strictest rule set.
- Start with your actual routine. Consider food access, cooking time, budget, culture, appetite, and how often you eat away from home.
- Choose a simple food-pattern change. For example, make a regular meal more substantial with vegetables, fruit, legumes, grains, dairy or fortified alternatives, and protein foods that suit you.
- Use a named diet only when it clarifies the next step. A Mediterranean-style pattern, DASH, plant-forward approach, lower-carbohydrate approach, or a higher-protein focus can each be useful frameworks—not identities to defend.
- Keep the safety boundary clear. Kidney disease, diabetes medication, pregnancy, an eating-disorder history, unexplained weight change, and serious digestive symptoms are reasons to get individual professional advice rather than self-prescribe a restrictive diet.
If you are considering a higher-protein approach, APH’s High Protein Diet for Weight Loss guide gives additional background. It does not replace personalised targets from a clinician or dietitian.
What Are the Most Common Diet Mistakes Adults Make?
- Starting with an extreme rule instead of a workable routine. A plan that disrupts every meal, social occasion, or budget is hard to keep.
- Treating a health claim as a personal diagnosis. A promising headline, wearable reading, or social-media story is not an individual assessment.
- Ignoring what a restrictive pattern leaves out. More restrictive diets can need more deliberate planning.
- Confusing a short-term change with a long-term answer. Review whether the pattern remains practical and enjoyable over time.
- Copying a diet meant for someone else’s medical context. Clinical diets and medication-related nutrition need individual guidance.
For a weight-loss-specific decision, use the separate Best Weight Loss Diet guide.
How Does Inflammation Fit Into Modern Diet Thinking?
Inflammation is a normal part of immune function. It is also a broad medical topic, not a diagnosis that can be made from a food list or a single symptom.
Diet is one part of overall health, alongside sleep, movement, stress, alcohol use, smoking, medication, and medical conditions. It is reasonable to focus on a varied, minimally processed food pattern, but no “anti-inflammatory” food list should be presented as treatment for a condition.
For a deeper general discussion, APH’s anti-inflammatory foods and seasonal-eating guides may be useful background. Seek qualified care for persistent symptoms or a diagnosed inflammatory condition.
Diet Finder: A Practical Starting Checklist
This is a non-medical checklist, not an interactive diagnostic tool. Start with the question that best matches your goal:
- I want a flexible, whole-food pattern: explore a Mediterranean-style or plant-forward starting point.
- Blood pressure is part of my clinical conversation: ask a clinician or dietitian whether DASH is appropriate; kidney disease and dialysis change the picture.[3][4]
- I want to lose weight: use the Best Weight Loss Diet guide, which is designed for that separate decision.
- I am drawn to fasting, keto, elimination, or another restrictive plan: first consider the food rules, nutrient gaps, medication implications, and whether the plan is sustainable.
- I have a diagnosed condition, take medication, am pregnant, have an eating-disorder history, or am worried about symptoms: get individual advice before making a major restriction.
Frequently Asked Questions
Q: What is the best diet for adults over 50?
There is no single best diet for every adult over 50. A practical starting point is a varied food pattern that fits appetite, food access, activity, health conditions, and preferences. Individual protein or calorie targets should not be guessed from a general article.
Q: Is time-restricted eating safe for everyone?
No. It is not appropriate to treat fasting as automatically safe. People who are pregnant or breastfeeding, have an eating-disorder history, use glucose-lowering medication, or have another relevant condition should get individual advice first.
Q: Do I need to follow a named diet?
No. Named diets are frameworks, not requirements. The 2025–2030 Guidelines describe a broad whole-food pattern that includes several food groups and can be adapted to different preferences.[1]
Q: Are healthy fats part of current guidance?
Yes. Current guidance includes a range of fats and oils while still advising that saturated fat should not exceed 10% of daily calories.[1] That is different from saying all fats—or all saturated-fat-rich foods—are interchangeable.
Q: What is a GLP-1-compatible diet?
It is informal language for nutrition support while a person uses GLP-1 therapy. The important point is coordinated care: medication management belongs with the prescriber, while a dietitian can help address food intake, side effects, and adequate nutrition.[5]
Q: How many carbohydrates should I eat?
This page does not prescribe a carbohydrate target. The Guidelines include whole grains, fruit, vegetables, dairy or fortified alternatives, and legumes within an overall food pattern.[1]
Q: Is the Mediterranean diet still useful?
It remains a flexible way to organise meals around minimally processed foods. Whether it is a good fit depends on the person’s preferences, budget, culture, and health context.
Q: What does “ultra-processed” mean?
The term is used in several research and public-health frameworks. Instead of trying to classify every item perfectly, start with a practical question: does the overall pattern leave room for nutrient-dense foods and limit frequent foods high in added sugars or refined carbohydrates?
Q: Should I use a CGM if I do not have diabetes?
It may offer short-term behavioural feedback, but it is not an independent weight-management solution and it does not diagnose healthy people from normal after-meal variation.[6]
Q: How do I know whether a diet is working?
Look beyond a single number. Ask whether the pattern is nourishing, sustainable, and compatible with your health care. For symptoms, abnormal tests, medication questions, or significant weight change, involve a qualified professional.
Conclusion: What to Actually Do Next
This guide is a map, not a verdict. Start with a pattern of food choices you can realistically maintain, then use the diet-family sections to understand what changes each approach asks you to make.
- Choose one practical change that fits your week.
- Use weight-loss, fasting, low-carbohydrate, or higher-protein guides only when that is your actual goal.
- Do not turn a general guide into a medical diet plan.
- Get individual advice before a major restriction if you have a health condition, take medication, are pregnant, have an eating-disorder history, or have concerning symptoms.
References
- U.S. Department of Health and Human Services and U.S. Department of Agriculture. Dietary Guidelines for Americans, 2025–2030. https://cdn.realfood.gov/DGA.pdf
- U.S. Department of Health and Human Services and U.S. Department of Agriculture. Dietary Guidelines for Americans, 2020–2025. https://www.dietaryguidelines.gov/sites/default/files/2021-03/Dietary_Guidelines_for_Americans-2020-2025.pdf
- National Heart, Lung, and Blood Institute. DASH Eating Plan. https://www.nhlbi.nih.gov/health/dash-eating-plan
- National Kidney Foundation. The DASH Diet. https://www.kidney.org/kidney-topics/dash-diet
- Mozaffarian D, et al. Nutritional priorities to support GLP-1 therapy for obesity: A joint advisory. PubMed 40445127
- Continuous glucose monitoring in non-diabetic populations: a systematic review of observational and interventional studies with meta-analysis. PubMed 41588451
- Estruch R, et al. Primary Prevention of Cardiovascular Disease with a Mediterranean Diet Supplemented with Extra-Virgin Olive Oil or Nuts. PubMed 29897866
- Melina V, Craig W, Levin S. Position of the Academy of Nutrition and Dietetics: Vegetarian Diets. PubMed 25911342
- Effectiveness of low-carbohydrate diets on type 2 diabetes: A systematic review and meta-analysis of randomized controlled trials in Eastern vs. Western populations. PubMed 40930317
- Systematic Review and Meta-analysis of Randomized Clinical Trials Comparing Time-Restricted Eating With and Without Caloric Restriction for Weight Loss. PubMed 40298934
- Lennerz BS, et al. Behavioral Characteristics and Self-Reported Health Status among 2029 Adults Consuming a “Carnivore Diet.” PubMed 34934897
📂 Diet Frameworks
This article is part of the APH cluster. Use the links below to move between the pillar and child articles.
- YOU ARE HERE The Comprehensive Guide to Modern Diets: What Actually Works in 2026
- → The Carnivore Diet: A Complete Evidence-Based Guide
- → Elimination Diet: A Step-by-Step Guide to Identifying Food Sensitivities
- → Intermittent Fasting for Beginners: A Practical Evidence-Based Guide
- → Metabolic Flexibility: Train Your Body to Burn Fat for Fuel — A Practical Guide to the Metabolic Flexibility Diet
- → Vegan Diet Weight Loss: What the Evidence Actually Shows
- → The Complete Guide to Mediterranean Food: Dishes, Health Benefits, and What to Eat
- → Low Carb Diet for Weight Loss
- → The Ultimate Seasonal Eating Guide: Nourish Your Body Naturally Year-Round
- → The Ultimate Guide to the Liver Shrinking Diet (2026)