
10 Best Herbs for Eye Health: Benefits, Active Compounds, and How to Use Them

Last updated: October 28, 2026
In this guide
- Quick answer and limits
- What the evidence can and cannot tell us
- Food-first context: what belongs on the plate
- How to use this guide safely
- Make the food-first approach repeatable
- 1. Bilberry
- 2. Ginkgo biloba
- 3. Eyebright
- 4. Turmeric
- 5. Green tea
- 6. Rosemary
- 7. Fenugreek
- 8. Hawthorn
- 9. Sage
- 10. Ginseng
- Saffron: human-trial context
- When not to self-manage
- The bottom line
Quick Answer: promising compounds are not proven eye treatments
Herbs and spices can be enjoyable parts of a varied diet, but the evidence does not show that any herb in this guide prevents or treats glaucoma, diabetic retinopathy, cataracts, floaters, or age-related macular degeneration (AMD). A few small human trials have tested particular extracts in particular diagnosed populations. Those findings cannot be assumed to apply to tea, culinary use, another product, or a different eye concern.
Written by Dave James. Dave is an independent health writer, not an eye-care clinician. This educational guide has not been clinically reviewed by an ophthalmologist or optometrist; it explains the evidence and its limits, not a treatment plan.
Key Takeaways
- Bilberry: human evidence for normal night vision is mixed to negative; a systematic review found the more rigorous trials did not support a benefit in healthy people.
- Ginkgo: small studies exist, but a Cochrane review concluded research had not answered whether it prevents AMD progression. It should not be used to self-manage glaucoma.
- Eyebright, rosemary, hawthorn and sage: traditional use or laboratory findings are not clinical evidence of eye benefit.
- Turmeric, green tea, fenugreek and ginseng: their eye-specific evidence is mostly preliminary, animal research, or limited clinical research—not proof of prevention or treatment.
- Saffron: small trials in people with diagnosed mild/moderate AMD reported changes in retinal functional measures. This is encouraging but does not establish disease prevention, replace AREDS2 advice, or make culinary saffron an AMD treatment.
- Food, tea, extracts and eye drops are different interventions. Do not put homemade herbal preparations in or near the eye.
What the evidence can—and cannot—tell us
Oxidative stress and inflammation are studied in many eye diseases, but a plausible mechanism is not the same as a demonstrated patient outcome. A cell study may show an antioxidant effect; an animal study may show a retinal signal; and a human trial may test a standardized extract at a defined dose. None of those automatically proves that a kitchen spice, tea, or general supplement will preserve vision or prevent disease.
For people with diagnosed AMD, glaucoma, diabetic eye disease, cataracts, persistent dry eye or another eye condition, the useful next step is an eye-care professional’s advice. The AREDS/AREDS2 findings apply to specific formulations and specific AMD risk groups—not to this herb list or to everyone seeking prevention.
Food-first context: what belongs on the plate
The strongest practical lesson from eye-health nutrition research is not to chase a single “vision herb.” A varied food pattern gives the body a broad mix of nutrients and is easier to sustain than a supplement stack. The National Eye Institute notes that green leafy vegetables are food sources of lutein and zeaxanthin, and that high-dose AREDS2 formulations are specific products for specific AMD risk groups—not a general prevention formula or a substitute for meals.
That creates a useful boundary for this article: food can be a sensible foundation for general wellbeing; herbs and extracts require much more care because their eye-specific evidence is usually narrower.
| Food group | Useful nutrient context | Low-fuss ways to include it |
|---|---|---|
| Dark leafy vegetables | Food sources of lutein and zeaxanthin. | Fold into eggs, soups, stir-fries or a salad rather than relying on a powdered greens product. |
| Eggs | Egg yolks also contain lutein and zeaxanthin, alongside protein and other nutrients. | Use in an omelet with greens, a grain bowl, or a simple breakfast if eggs suit your diet. |
| Fish and seafood | Oily fish supply omega-3 fats; food patterns matter more than a single food. | Use salmon, sardines, trout or another preferred fish in ordinary meals; choose alternatives that suit personal needs. |
| Colourful vegetables and fruit | They add carotenoids, vitamin C and a range of plant compounds. | Rotate peppers, tomatoes, carrots, citrus, berries and whatever is affordable and appealing. |
| Nuts, seeds, beans and lentils | They contribute minerals, fats, protein and fibre within a varied diet. | Add a handful, a spoonful or a serving to meals rather than treating them as a clinical intervention. |
One realistic food-first day: eggs with greens and berries at breakfast; a lunch built around beans, vegetables and a protein of choice; fish or another protein with colourful vegetables at dinner; and nuts, fruit or yoghurt as an optional snack. This is an example of variety, not a prescription, and it is not a treatment for an eye condition.
For broader meal ideas, see APH’s guides to nutrient-dense foods and polyphenol-rich foods. They expand the food side of the discussion without pretending that a food list replaces eye care.
How to use this guide safely
Readers usually arrive here with one of three different questions. Choosing the right lane prevents a general herb article from becoming accidental self-treatment.
Use the food-first section. Build meals around variety and familiar foods; do not expect a visible change in vision from an ingredient.
Use the evidence sections to ask better questions at an eye-care appointment. Do not select an herb or extract as a substitute for monitoring or prescribed care.
Start with the urgent-symptom section, not a supplement. Sudden or changing vision symptoms need an eye-care assessment.
Food, tea, extract and eye drop are not interchangeable
- A food or culinary spice is part of an ordinary eating pattern. It is not equivalent to a concentrated product used in a trial.
- A tea can vary widely in plant amount and active compounds; it is not automatically a standardised extract.
- An extract may have a named dose and formulation, but a study of one extract in one population does not validate every bottle on a shelf.
- An eye drop must be a sterile ophthalmic product. A homemade preparation should never be used in or near the eye.
A five-question label check before buying an eye supplement
- Was the product—or a closely matching standardised preparation—tested in humans?
- Who was studied: healthy adults, people with a diagnosed condition, or animals/cells?
- What outcome changed: a symptom score, a visual-function measure, an imaging marker, or a meaningful clinical outcome?
- How long was the study, and was there a placebo/control group?
- Could the product interact with medicines or be unsuitable in pregnancy, before surgery or with an existing condition?
If those questions cannot be answered clearly, the honest conclusion is not “it works.” It is “the evidence is not strong enough to guide a purchase.”
Questions that make an eye-care appointment more useful
If an eye concern is already being monitored, it can help to take a short written list rather than relying on a supplement label. Examples:
- What is the exact diagnosis, if any, and what changes should prompt earlier review?
- Does my current care include a recommended nutrition approach or an AREDS2 formulation for my situation?
- Is this proposed herb or supplement compatible with my medicines and planned procedures?
- Which outcome should I realistically monitor, and when should I stop a product and contact the practice?
This keeps the decision with the clinician who can examine the eye and interpret a person’s full history. The herbs below are best read as a transparent research summary, not answers to those questions.
Make the food-first approach repeatable
The practical challenge is rarely identifying one “good” ingredient. It is making a varied pattern easy enough to repeat on ordinary weeks. A short grocery template can do more than an expensive supplement stack because it lowers the number of decisions needed at each meal.
- Choose two leafy or green vegetables you will genuinely cook or eat.
- Choose two other colours of produce, fresh or frozen, to rotate through meals.
- Choose a convenient protein base—eggs, fish, beans, lentils, dairy, meat or another preferred option.
- Keep one easy whole-food snack option such as fruit, yoghurt, nuts or seeds.
- Use herbs and spices for flavour, not as a promise of a medical effect.
This is deliberately flexible. Cost, culture, allergies, digestion, medication needs and food access all affect what makes sense. A frozen vegetable, canned fish or basic egg meal can be more repeatable than a “perfect” menu that never makes it into the week.
How to avoid turning healthy habits into a supplement experiment
When changing food habits, add one or two repeatable foods rather than trying to track every compound. Do not use subjective day-to-day vision changes as proof that an herb is working or failing. If a supplement is being considered anyway, keep the label or a photo of it, discuss it with a pharmacist or clinician, and avoid starting several products at once. That makes interactions and side effects harder to recognise.
For the wider nutrition picture, APH’s foods and herbs evidence guide explains why dietary patterns deserve more attention than “superfood” claims. This page stays focused on the narrower question: what eye-specific herb research does—and does not—show.
1. Bilberry: limited and mixed human evidence
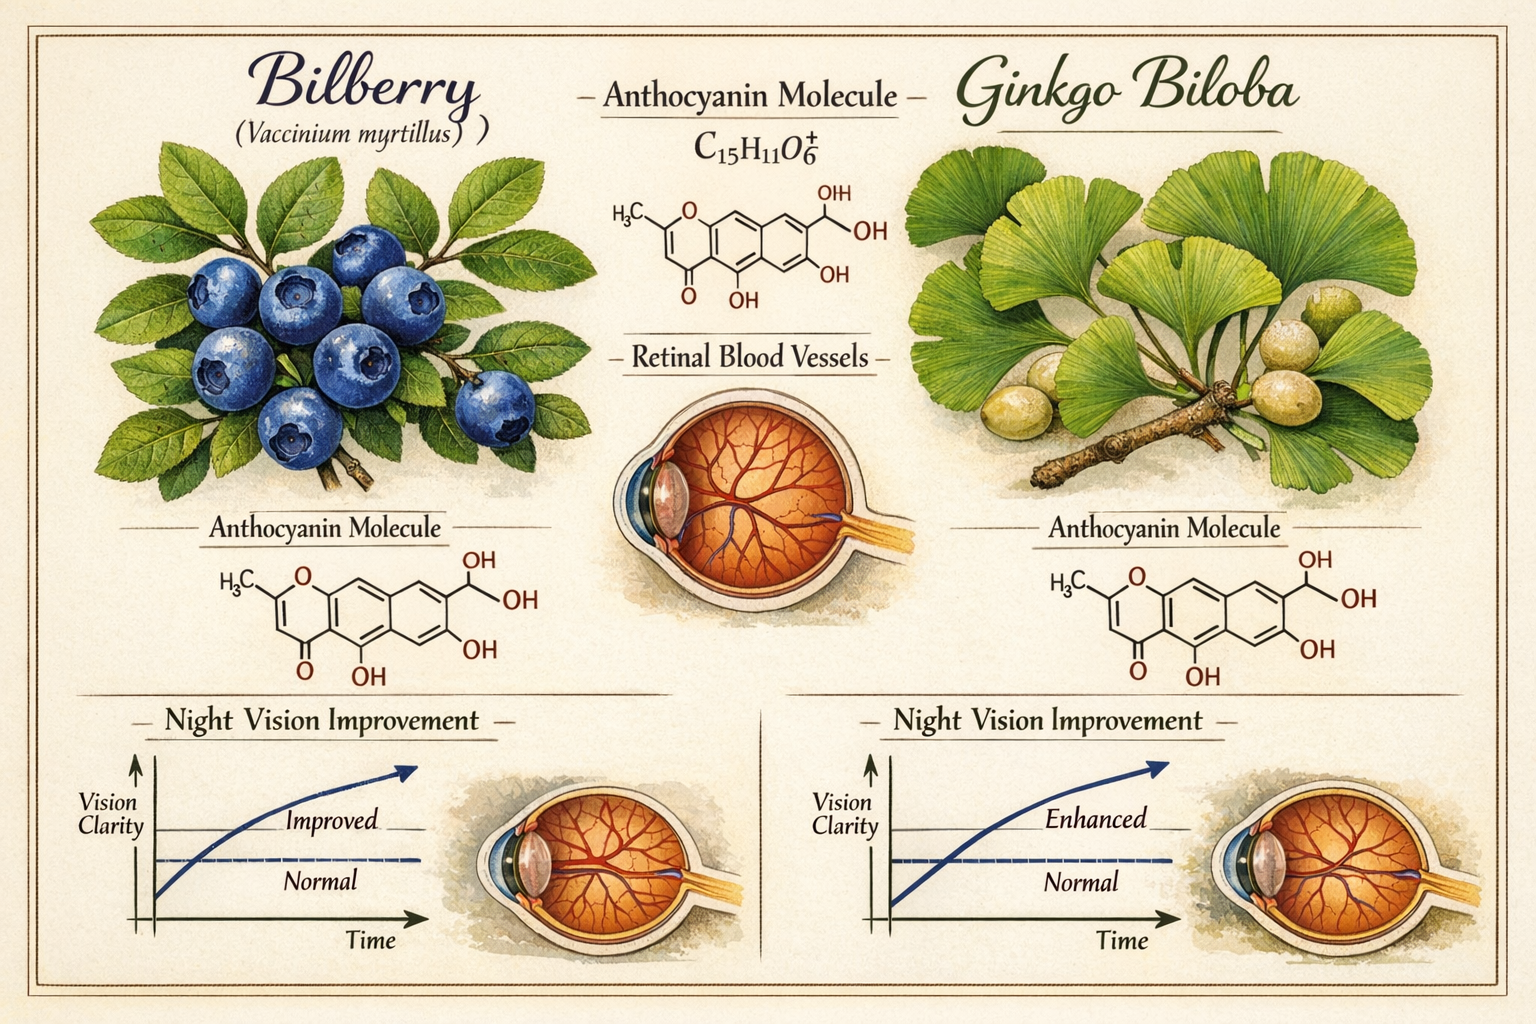
Bilberry (Vaccinium myrtillus) contains anthocyanins. It is often promoted for night vision, but the evidence needs more caution than that reputation suggests.
- Population and preparation studied: in a small double-blind crossover trial, 15 healthy young men received a bilberry extract containing 25% anthocyanosides for three weeks.
- Outcome: the trial did not find improved night visual acuity or night contrast sensitivity. A systematic review likewise found that the more rigorous placebo-controlled trials did not support improved normal night vision.
- Important limitation: an 8-week trial in selected office workers tested a 480 mg/day extract for display-terminal eye fatigue; that is not evidence for treating eye disease, floaters or poor night vision in general.
Practical reading: enjoy bilberries or similar berries as food if you like them. Do not rely on bilberry to improve night driving, prevent retinal disease, or treat visual changes.
2. Ginkgo biloba: small studies, unresolved clinical question
Standardized Ginkgo biloba extracts have been studied for vascular and antioxidant hypotheses. A small trial in normal-tension glaucoma and other limited studies measured visual-field or contrast outcomes, but these are not a basis for recommending ginkgo for glaucoma or for changing prescribed care.
- Population and preparation: small studies have evaluated standardized extracts in people with diagnosed eye conditions.
- Outcome: a Cochrane review identified only two small AMD trials (119 people total) and concluded the question of whether ginkgo prevents AMD progression had not been answered.
- Limitations: small samples, short follow-up and inconsistent outcomes. No conclusion can be extended to prevention in otherwise healthy people.
Safety: ginkgo supplements may interact with anticoagulant or antiplatelet medicines and other drugs. Discuss supplements with the clinician or pharmacist who knows your medications.
3. Eyebright: tradition is not proof
Eyebright (Euphrasia) has a long history of traditional use for eye complaints. The often-cited human study was a prospective cohort study of a specific single-dose eyedrop preparation for conjunctivitis—not a blinded randomised trial and not evidence for home remedies, dry eye, screen fatigue or infection treatment.
Important safety boundary: never place homemade teas, washes, tinctures or plant material in or near the eye. A non-sterile preparation can introduce contamination or worsen irritation. Redness, discharge, pain, light sensitivity or a suspected infection needs professional assessment rather than an herbal eye product.
4. Turmeric: eye-specific use remains unproven
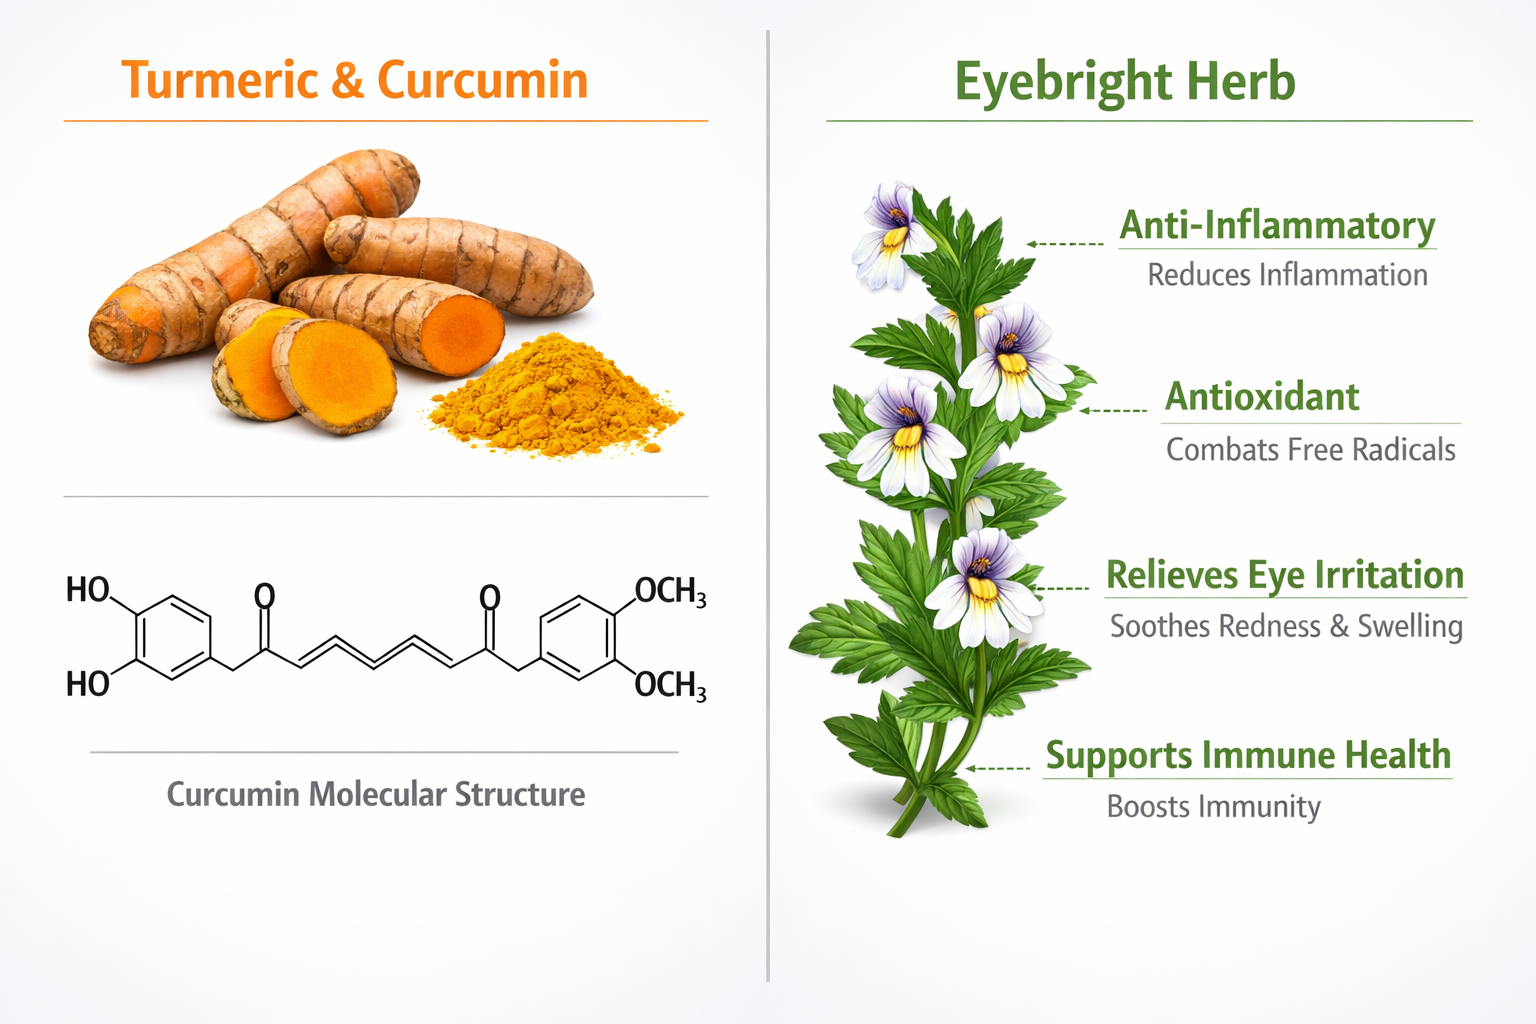
Turmeric (Curcuma longa) contains curcuminoids including curcumin. Laboratory and animal research on inflammation is not proof of clinical benefit for uveitis, dry eye, glaucoma or diabetic retinopathy. The U.S. National Center for Complementary and Integrative Health says there is not enough evidence to definitively conclude that oral turmeric or curcumin benefits health conditions generally.
- Preparation matters: cooking with turmeric is not equivalent to a concentrated, bioavailability-enhanced curcumin product.
- Limitations: formulations vary greatly; adding piperine changes absorption and may change medication interactions.
- Safety: highly bioavailable curcumin products have been linked with liver harm in some people. Get personalised advice before using a supplement, especially with medication or liver/gallbladder concerns.
5. Green tea: animal tissue data, not a human eye-treatment trial
Green tea (Camellia sinensis) contains catechins. A 2010 study found that catechins from green tea extract reached tissues of rats’ eyes and altered oxidative-stress markers. That does not demonstrate better vision, lower eye pressure or protection from cataracts in people.
Green tea as a beverage is different from a concentrated extract. NCCIH notes that beverage use has not raised major safety concerns for adults, while extracts can cause side effects and, uncommonly, liver injury. Do not use an extract as an eye treatment without advice from a qualified clinician.
6. Rosemary: experimental retinal findings only
Rosemary contains compounds such as carnosic acid and rosmarinic acid. Retinal cell and animal experiments are useful for generating hypotheses, but there are no robust human trials showing that rosemary tea, food use or supplements protect the retina, improve circulation, or slow AMD.
Evidence grade: experimental/preclinical. Culinary rosemary is a flavouring, not an eye treatment.
7. Fenugreek: animal diabetic-retina research is not a recommendation
Fenugreek (Trigonella foenum-graecum) has been studied in a streptozotocin-induced diabetic rat model, where investigators measured retinal oxidative, inflammatory and vascular markers. This does not show that fenugreek prevents diabetic retinopathy in people or replaces blood-glucose management and eye screening.
Evidence grade: preclinical for eye outcomes. People using glucose-lowering or anticoagulant medicines should seek individual professional advice before using a fenugreek supplement.
8. Hawthorn: no established eye-health outcome
Hawthorn is often discussed in cardiovascular herbal traditions. That does not establish that it improves ocular blood flow, prevents hypertensive retinopathy, or protects the optic nerve. We could not identify reliable human clinical evidence for those eye-specific outcomes.
Evidence grade: insufficient for eye-health claims. Hawthorn can interact with cardiovascular medicines; do not add a supplement to manage an eye or blood-pressure concern without medical advice.
9. Sage: mechanism evidence is not patient evidence
Sage contains compounds also found in rosemary, including rosmarinic acid. A laboratory mechanism such as VEGF signalling is not evidence that culinary sage or a supplement prevents wet AMD, diabetic retinopathy or other retinal disease.
Evidence grade: insufficient for eye-health claims. Use as a culinary herb if appropriate for you; do not treat eye symptoms with sage supplements or eye preparations.
10. Ginseng: one small pilot is not clinical proof
Ginseng contains ginsenosides and has attracted laboratory research. A 2026 randomised pilot in 24 people with mild-to-moderate non-proliferative diabetic retinopathy reported short-term, region-specific changes in OCT angiography perfusion metrics after Korean red ginseng extract. It found no significant changes in visual acuity, retinal thickness, diabetic-retinopathy stage or diabetic macular oedema over three months.
Evidence grade: early human signal with no demonstrated disease-modifying clinical outcome. This does not support ginseng for optic-nerve protection, glaucoma, or diabetic-retinopathy treatment. Ginseng can interact with medicines, including diabetes and blood-thinning medicines.
Saffron: the clearest human-trial signal, still not a self-treatment
Saffron (Crocus sativus) deserves separate treatment because several small trials studied a specific oral supplement in people already diagnosed with AMD—not culinary saffron in the general population.
- Early AMD trial: 25 people received saffron 20 mg/day or placebo for three months in a crossover design. Retinal flicker-sensitivity measures improved after the supplement; the authors said the clinical significance still needed evaluation.
- Mild/moderate AMD trial: a 100-person randomised, double-blind, placebo-controlled crossover study reported modest visual-function improvement. A later open-label extension followed 93 adults taking 20 mg/day for 12 months and reported modest multifocal-electroretinogram changes.
- Limits: these studies do not show prevention of AMD, reversal of vision loss, or a substitute for monitoring and treatments. They also do not establish an equivalent effect from saffron in cooking.
If you have AMD, ask your ophthalmologist or optometrist before adding any supplement. Follow any personalised AREDS2 advice from your eye-care team rather than self-prescribing from an online list.
When not to self-manage eye symptoms
For non-urgent concerns such as recurring irritation, dry-eye symptoms, screen discomfort or trouble seeing at night, an eye examination can identify treatable causes such as prescription changes, ocular-surface disease or other conditions. Supplements should never delay that assessment.
Evidence context—not a symptom-to-herb matcher
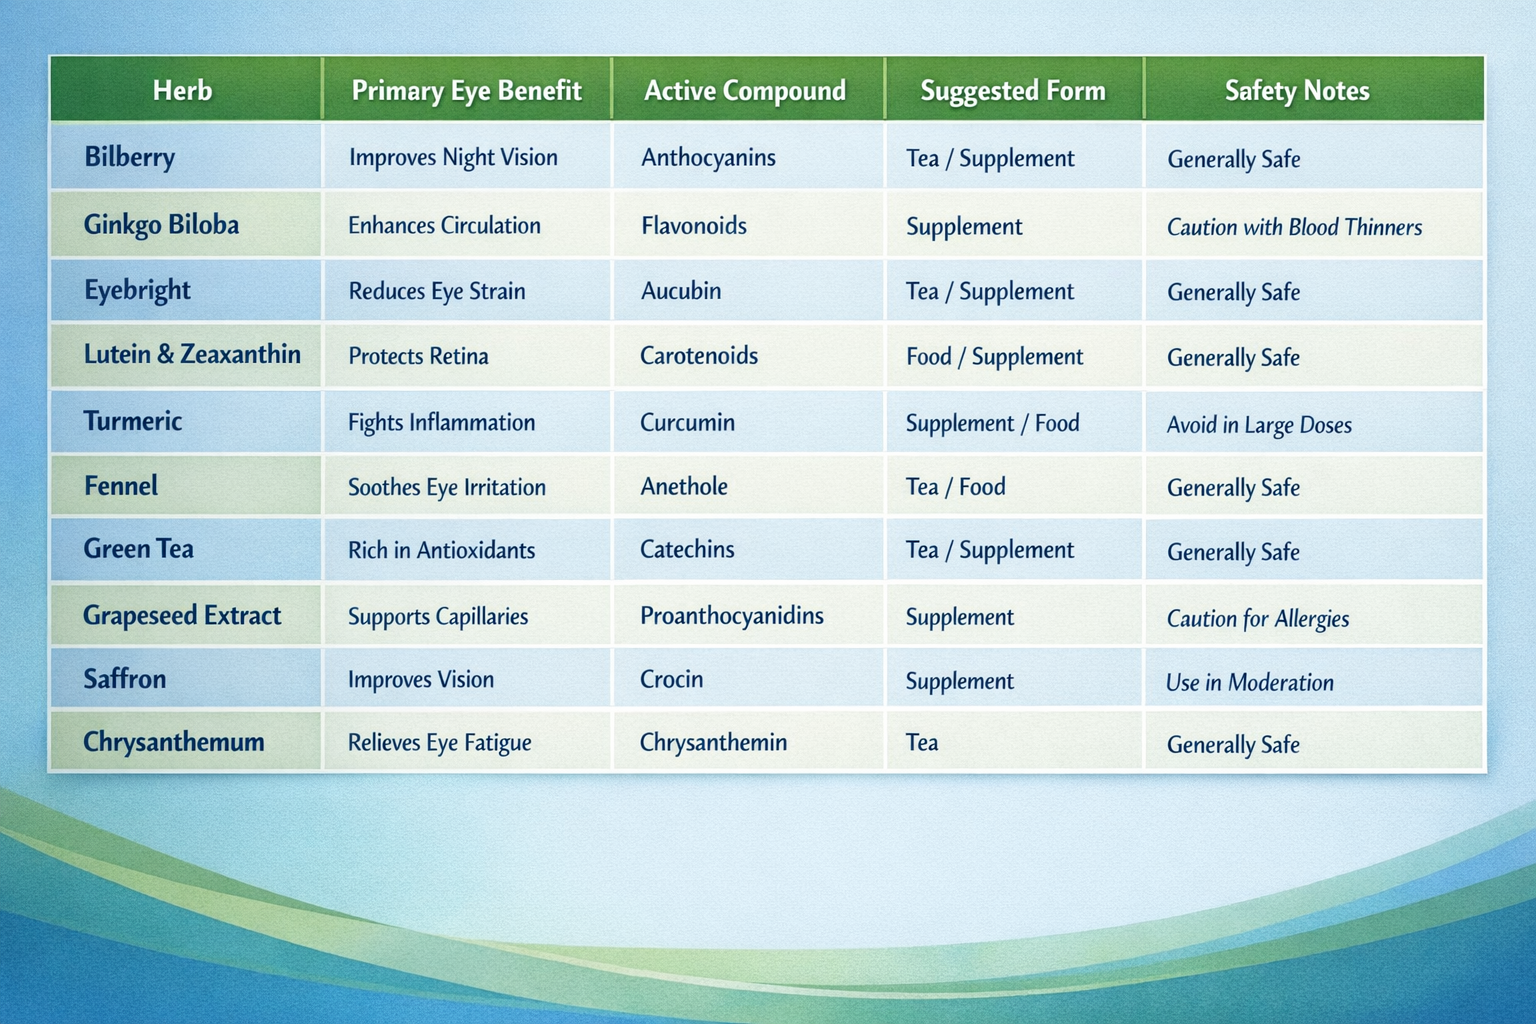
| Herb / compound | Best available eye-specific evidence | What it does not establish |
|---|---|---|
| Bilberry | Mixed human studies; rigorous studies did not support improved normal night vision. | Night-driving improvement, floaters treatment, or retinal-disease prevention. |
| Ginkgo | Small studies in diagnosed populations; AMD evidence remains inconclusive. | Glaucoma treatment, lower eye pressure, or disease prevention. |
| Eyebright | Traditional use and a non-randomised study of one sterile eyedrop preparation. | Home eye drops, infection treatment, or dry-eye management. |
| Turmeric, green tea, rosemary, fenugreek, hawthorn, sage | Mostly laboratory, animal, or non-eye-specific evidence. | Clinical eye benefit from food, tea or supplement use. |
| Ginseng | One small 2026 pilot measured selected retinal-imaging metrics. | Improved vision or slower diabetic-retinopathy progression. |
| Saffron | Small human AMD trials of defined oral supplements measured modest functional signals. | AMD prevention, cure, or equivalence with culinary saffron. |
Common mistakes when using herbs for eye health
- Turning a mechanism into a treatment claim. Antioxidant activity in a lab does not show a person’s vision will improve.
- Equating tea or food with a trial extract. Product, dose, standardisation and study population all matter.
- Using herbs for a diagnosed eye disease. Do not replace eye examinations, prescribed treatment or personalised AREDS2 advice.
- Putting non-sterile products in the eye. Homemade preparations can be unsafe.
- Ignoring interactions. Discuss supplements with a pharmacist or clinician when you take medicines or are pregnant, breastfeeding, preparing for surgery, or managing a condition.
Frequently Asked Questions
Q: Which herb is best for night vision?
No herb has reliable evidence of improving normal night vision. Bilberry is widely marketed for this purpose, but the more rigorous trials reviewed did not support that claim in healthy people.
Q: Can herbs lower eye pressure or treat glaucoma?
No. Do not use herbs to lower eye pressure or manage glaucoma. Small ginkgo studies do not replace clinically proven pressure management, monitoring or prescribed treatment.
Q: Can herbs get rid of floaters?
No herb has been shown to remove floaters. Sudden new floaters, flashes, a shadow or blurred vision need prompt eye-care assessment.
Q: Is saffron proven to treat AMD?
No. Small trials of specific oral saffron supplements in people with diagnosed AMD found modest changes in some functional measures. That is not proof of prevention, cure, or a replacement for eye-care advice and treatment.
Q: Is green tea good for eye health?
Green-tea catechins reached eye tissues in a rat study, but that does not prove an eye benefit in people. Green tea as a beverage and concentrated extracts have different safety profiles.
Q: Are herbal eye drops or compresses safe?
Do not put homemade herbal liquids in or near your eyes. Use only products specifically prepared as sterile ophthalmic products, and seek care for pain, redness, discharge, injury or vision change.
The Bottom Line
The credible conclusion is narrower than a typical “best herbs” list: several plants contain interesting compounds, but eye-specific clinical evidence is limited and often preliminary. Saffron has the clearest small-trial signal in diagnosed AMD; bilberry and ginkgo have mixed or inconclusive evidence; and many other claims rest mainly on laboratory or animal work.
Enjoy herbs and spices as food if they suit you, but do not use them as substitutes for eye examinations, medical treatment, or urgent assessment of new visual symptoms. A transparent limit is more useful than a long list of promises.
More great articles that may be of interest to you 🙂
10 Natural Herbs To Get Rid Of Headaches
References & Research Sources
These sources are provided so readers can check the population, preparation and outcome for themselves. Inclusion does not turn a study finding into a recommendation.
- Canter PH, Ernst E. Anthocyanosides of Vaccinium myrtillus (bilberry) for night vision—a systematic review of placebo-controlled trials. PubMed.
- Muth ER, Laurent JM, Jasper P. The effect of bilberry nutritional supplementation on night visual acuity and contrast sensitivity. PubMed.
- Ozawa Y, et al. Bilberry extract supplementation for preventing eye fatigue in video display terminal workers. PubMed.
- Evans JR. Ginkgo biloba extract for age-related macular degeneration. Cochrane review. PubMed.
- Quaranta L, et al. Effect of Ginkgo biloba extract on preexisting visual field damage in normal tension glaucoma. PubMed.
- Stoss M, et al. Prospective cohort trial of Euphrasia single-dose eye drops in conjunctivitis. PubMed.
- National Center for Complementary and Integrative Health. Turmeric: Usefulness and Safety. NCCIH.
- Chu KO, et al. Green tea catechins and their oxidative protection in the rat eye. PubMed.
- Gupta SK, et al. Effects of fenugreek on retinal oxidative stress and biomarkers in streptozotocin-induced diabetic rats. PubMed.
- Lee DH, et al. Effect of Korean red ginseng on deep capillary plexus parameters in diabetic retinopathy. PubMed.
- Falsini B, et al. Influence of saffron supplementation on retinal flicker sensitivity in early age-related macular degeneration. PubMed.
- Broadhead GK, et al. Saffron therapy for mild/moderate AMD: a randomised clinical trial. PubMed.
- Broadhead GK, et al. Saffron therapy for the ongoing treatment of AMD. PubMed.
- National Eye Institute. Floaters. NEI.
- National Center for Complementary and Integrative Health. Eye Conditions and Complementary Health Approaches. NCCIH.
- National Eye Institute. AREDS/AREDS2 Frequently Asked Questions. NEI.

Dave James has spent 30+ years reading health and longevity research, and has run All Perfect Health for the past five. His background is in Australian mining and industrial engineering — disciplines built on questioning claims, measuring outcomes, and respecting evidence. He writes about what the research actually says, including where the experts disagree.
More about Dave & this site →
Part of the Herbs & Targeted Support cluster
📂 10 Best Herbs for Eye Health
This article is part of the APH cluster. Use the links below to move between the pillar and child articles.
- YOU ARE HERE 10 Best Herbs for Eye Health: Benefits, Active Compounds, and How to Use Them
- → Herbs for Digestion: Natural Remedies for Bloating, Gas, and Gut Comfort
- → Health Benefits of Ginger: Digestion, Inflammation, and Immunity
- → Adaptogenic Herbs for Stress and Resilience: Ashwagandha, Rhodiola, and Holy Basil